Autoimmune gastritis impairs iron and B12 absorption. Until it is found, a well-managed thyroid is not enough to feel well.
A thyroid panel and a standard blood count do not diagnose autoimmune gastritis, an immune attack on the acid-producing cells of the stomach. It is about five times more common in people with autoimmune thyroid disease. That includes both Hashimoto's and Graves' disease. It often surfaces as iron deficiency that does not correct, with B12 deficiency following later.
The fatigue, brain fog, and cold intolerance that low iron and low B12 cause read much like an under-treated thyroid. Post-meal fullness, when it shows up, gets filed as a separate stomach problem. One condition can be the root cause of all of it, and it is rarely the one being looked for.
A woman whose TSH is in range and still feels depleted is told her thyroid is handled. That is accurate, and the investigation usually ends there.
Up to 30 percent of patients have no symptoms when the diagnosis is made. Among those who do, the pattern tends to be fullness and discomfort after eating rather than pain.
Digestive symptoms appear about three times more often in patients without anemia. So the women with the clearest stomach complaints are often the ones whose blood count looks normal. Raise unexplained upper digestive symptoms with your provider if you have an autoimmune thyroid condition. That holds even when your iron and blood counts come back fine.
A thyroid panel and an annual physical are not designed to detect it.
| On a routine thyroid and blood workup | Tests used to identify autoimmune gastritis |
|---|---|
| TSH | Parietal cell antibody |
| Free T4 | Intrinsic factor antibody |
| Thyroid antibodies | Gastrin |
| Hemoglobin | Pepsinogen I and the pepsinogen I to II ratio |
| Average red-cell size | Upper endoscopy with samples |
Autoimmune gastritis is about five times more common in people with autoimmune thyroid disease than in people without it. That includes both Hashimoto's and Graves' disease.
Five times more common is still uncommon. Most women with Hashimoto's do not develop autoimmune gastritis. The reason to rule it out is the cost of missing it. The iron and B12 deficiencies it causes keep returning no matter how well the thyroid is managed.
Among 840 people with Hashimoto's, 21.4 percent carried antibodies against the acid-producing cells of the stomach. The figure for adults without autoimmune thyroid disease runs 2 to 12 percent.
That is not the same as 21.4 percent having the disease. Plenty of people carry the antibody and never develop the condition. Over five years, 24 percent of antibody-positive Hashimoto's patients with no symptoms developed autoimmune gastritis. The antibody identifies who needs further testing.
The leading explanation involves an H. pylori infection. It may prime the immune system against a bacterial protein closely resembling one in the stomach lining, with shared genetic susceptibility doing the rest. Researchers have not established that as the cause. The resemblance has been shown in the laboratory. Whether treating H. pylori changes the course of autoimmune gastritis has not been tested in a trial.
Iron deficiency is often one of the earliest clues to autoimmune gastritis, especially when a standard iron supplement does not correct it.
Stomach acid releases iron bound up in food and converts it into the form the small intestine can absorb. When the stomach makes too little acid, the body may not absorb enough iron from a standard supplement to correct the deficiency.
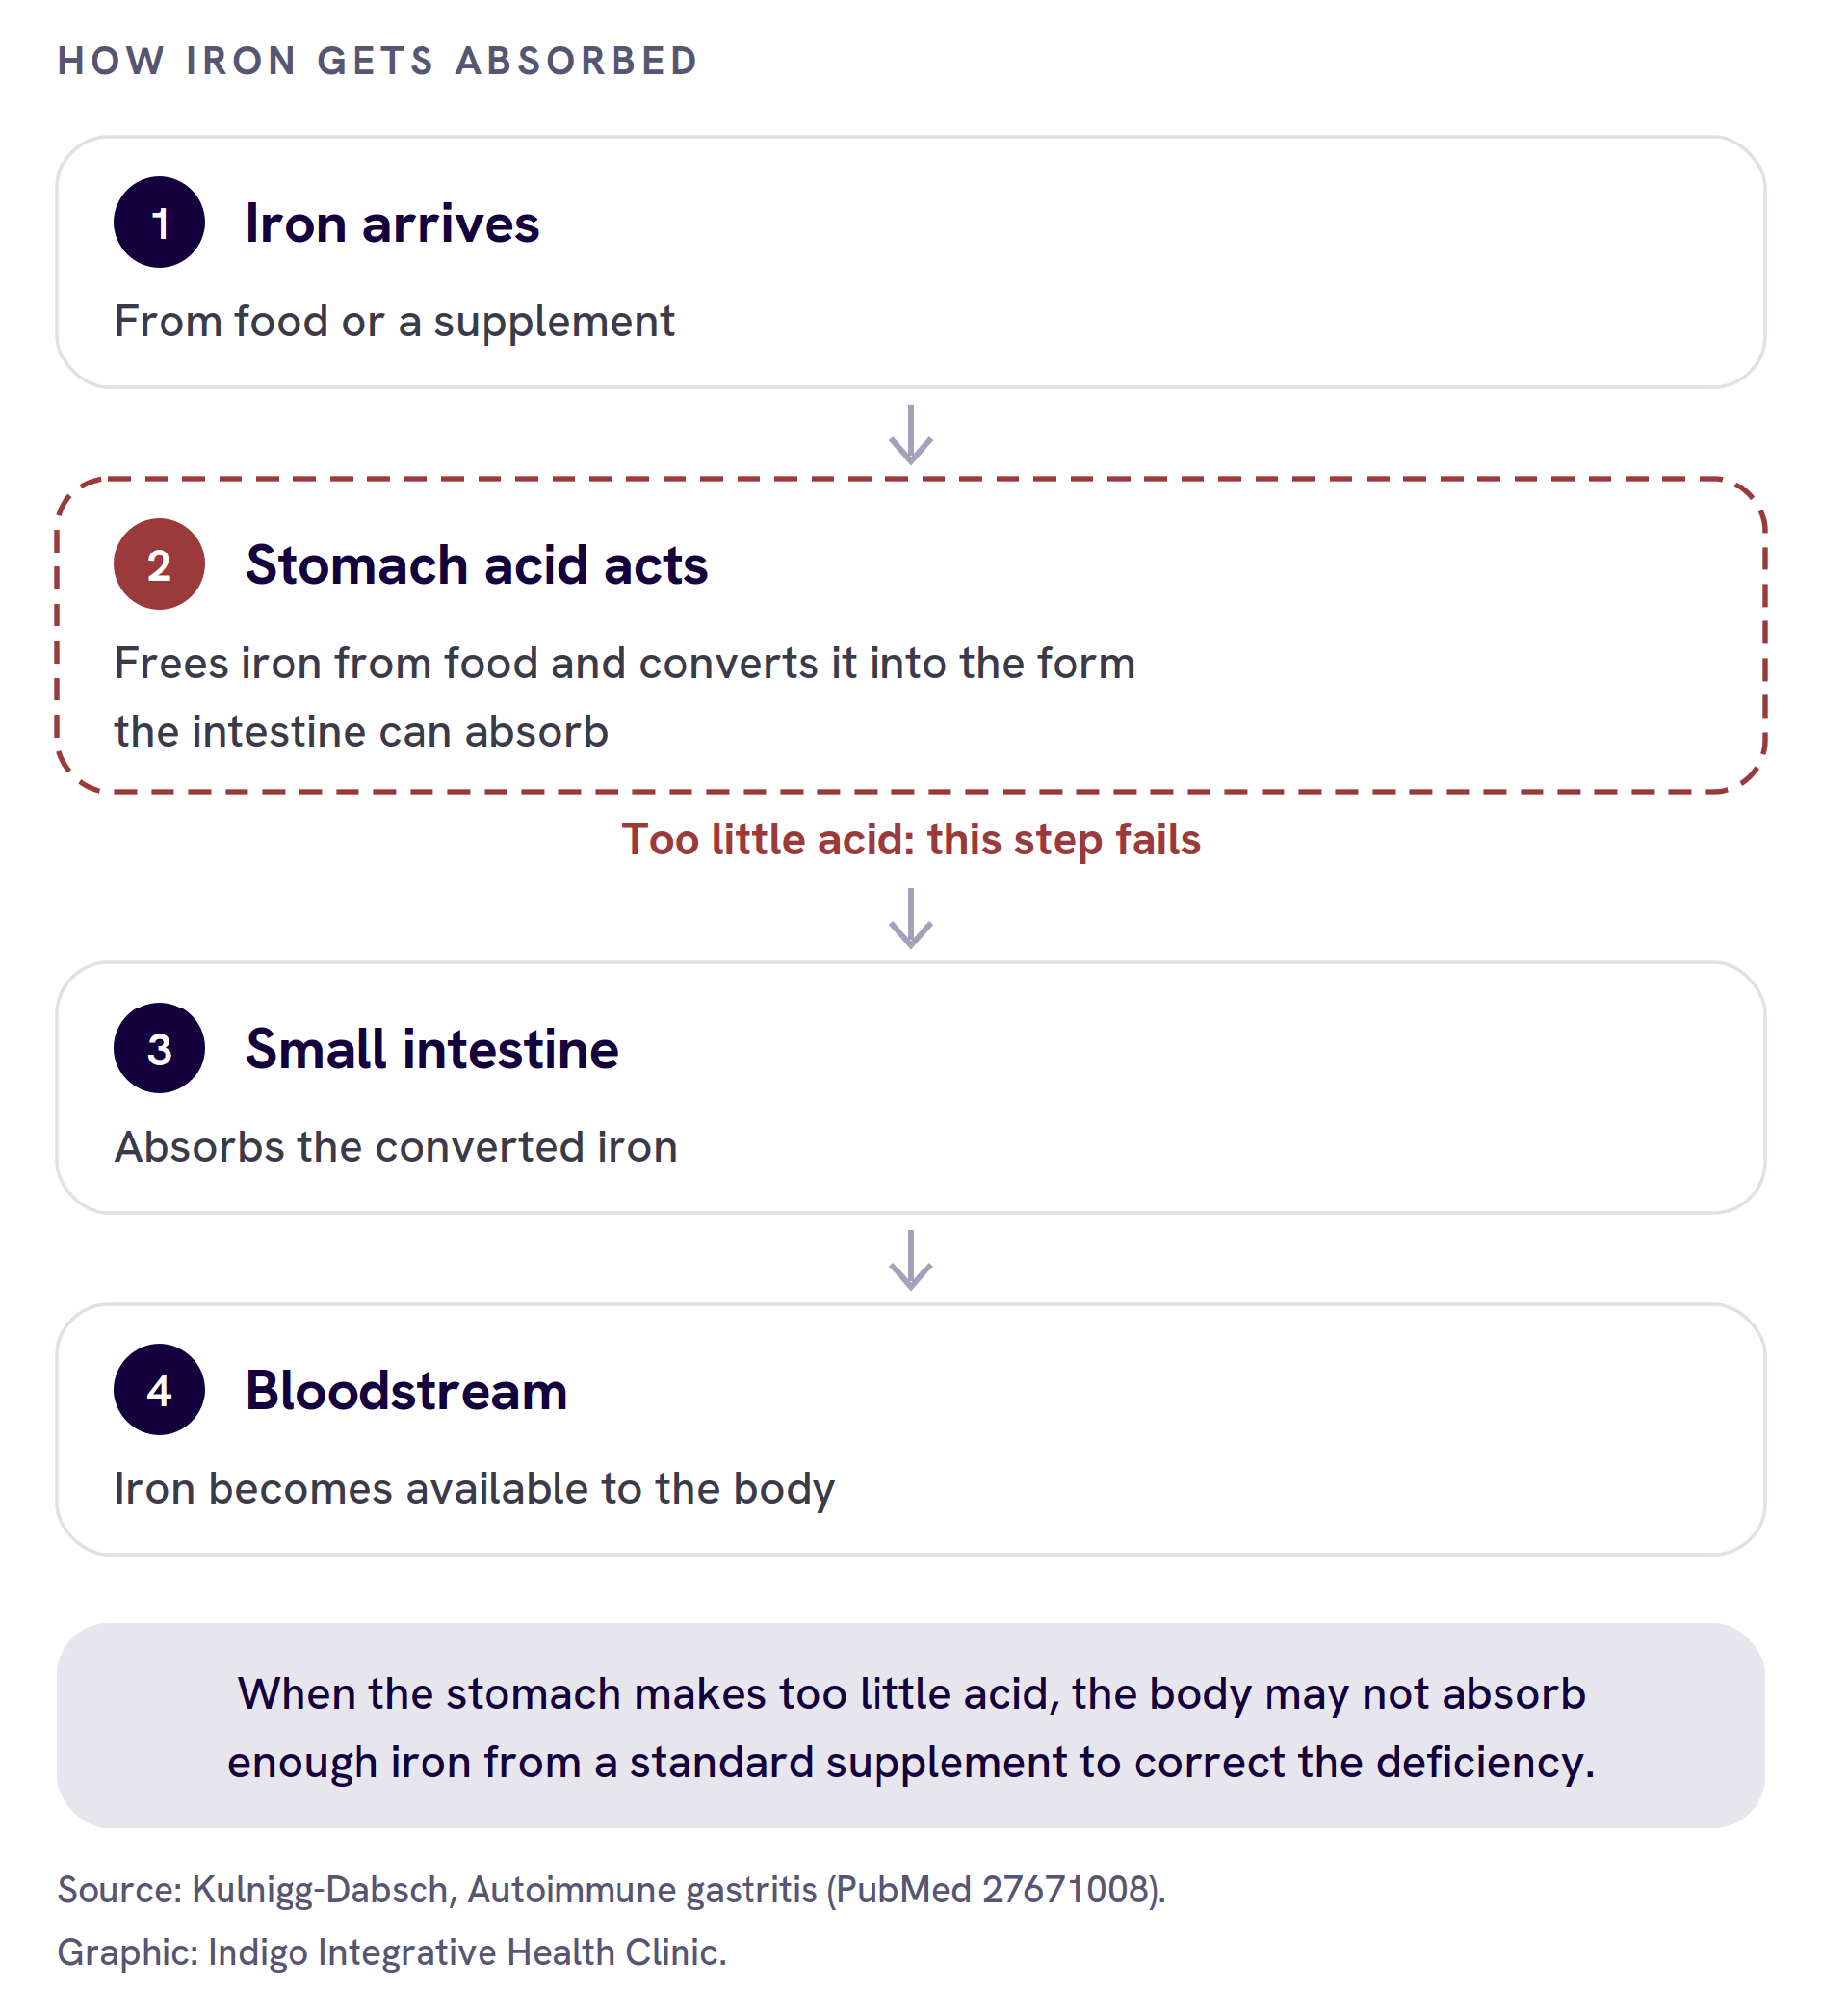
Some iron deficiency anemia has no explanation after a standard workup. Autoimmune gastritis accounts for 20 to 27 percent of those cases. Roughly 70 percent of that group does not respond adequately to oral iron. Those figures come from specialist clinics seeing already-unexplained iron deficiency cases, not from women whose low iron has an obvious cause.
In one study of 160 people with autoimmune gastritis, those whose first sign was iron deficiency were about 41 years old on average. Those whose first sign was B12 deficiency were about 62. Everyone in that study was measured once, at the point they came in, rather than followed over the years. The gap between those two ages still suggests the same order: iron runs low first, B12 later.
Failing standard oral iron does not automatically mean infusions are needed. In patients with autoimmune gastritis or H. pylori gastritis, an oral formulation designed to release iron past the stomach left fewer people needing an infusion. It was a case-control study rather than a randomized trial, so the size of that difference is uncertain.
Indigo does not offer iron infusions. We refer out for that when necessary.
Autoimmune gastritis causes the stomach to make too little acid, not too much. Fullness after eating is still an acid problem, but it is the opposite of the one most people assume.
Post-meal fullness can look like ordinary reflux. An acid-blocking medication called a proton pump inhibitor often gets started before this diagnosis is made. Those drugs lower stomach acid further in a stomach already making too little. That can make iron and B12 absorption worse. If you are on a prescribed acid-blocking medication, talk to your treating clinician before changing anything.
Stomach acid also helps control bacteria. With less of it come bloating and irregular bowel habits. Those can look like irritable bowel syndrome or small intestinal bacterial overgrowth, also called SIBO. Both diagnoses can get made while the autoimmune gastritis goes unrecognized.
Low acid can also confuse H. pylori testing and cause false results. Other bacteria grow when acid is low, and they produce the same enzyme the breath test detects. That caused a false positive in 4 of 102 patients on acid-suppressing medication. Autoimmune gastritis can have the same effect. A woman may then be treated more than once for an infection she does not have.
Betaine hydrochloride, sold to replace missing acid, has not been shown to restore iron absorption in autoimmune gastritis. Two trials are now testing it directly, one randomized against placebo and a digestive enzyme. Until those studies report, supplemental acid should not replace a proper evaluation. Autoimmune gastritis carries a raised tumor risk, and its safety in an already-inflamed stomach lining has not been studied. Self-treating the symptom can also delay finding the condition underneath it.
Standard levothyroxine tablets need enough stomach acid to dissolve before the medicine can be absorbed. Impaired acid production has been linked to a 22 to 34 percent higher dose requirement.
That finding comes from patients with multinodular goiter rather than Hashimoto's, so the exact percentage may not transfer.
Switching to a liquid form of levothyroxine has helped some patients whose stomach makes too little acid.
A TSH that will not stay steady in someone taking her medication correctly is worth investigating rather than assuming she is skipping doses.
Nerve damage from B12 deficiency can begin before anemia appears, and a normal complete blood count does not always rule the deficiency out.
Two different timelines run through this condition. Across the condition as a whole, iron runs short first and B12 runs short years later. Within a B12 deficiency itself, nerve damage can begin before the blood count changes at all.
The complete blood count is the routine test that measures hemoglobin and the average size of your red blood cells. Both can read normal in someone whose B12 is already low enough to affect the nerves. Iron deficiency can also pull the average red-cell size back toward normal. That matters here, because iron and B12 deficiency often occur together in autoimmune gastritis.
The same cells that make stomach acid also make intrinsic factor, the protein required to absorb B12 further down the gut. Lose enough of them and pernicious anemia can follow.
Low B12 can damage the nerves in the spinal cord and elsewhere in the body. Waiting for the blood count to declare itself is how that gets missed. Methylmalonic acid and homocysteine can help clarify a borderline B12 result. Kidney function and the rest of the clinical picture also matter.
Around 1 percent of an oral B12 dose crosses the gut wall without intrinsic factor. That is why high-dose tablets are studied as an alternative to injections. The evidence is thin: three small trials, 153 people, low certainty, and people with true malabsorption were under-represented. Whether tablets are enough for someone with autoimmune gastritis has not been established.
Indigo offers B12 injections. Where absorption is impaired, that is the route we favor. An injection does not depend on how well the gut is taking B12 in. The decision still belongs with the treating clinician and the individual case.
Blood antibody testing is a first step, but it is not enough to diagnose autoimmune gastritis on its own. Some people with the antibodies do not have the condition, and some people with the condition do not test positive.
The intrinsic factor antibody is close to conclusive when it comes back positive, but it misses many true cases. The parietal cell antibody detects more cases, though it can also be positive in people who do not have autoimmune gastritis. A negative result on both tests does not always rule the condition out.
Gastrin often rises when the stomach cannot make enough acid. Pepsinogen I may fall, and the balance between pepsinogen I and II may change as autoimmune gastritis progresses.
An upper endoscopy with samples from different parts of the stomach can help confirm autoimmune gastritis and check for related problems. Doctors read those results together with the blood tests and the medical history.
One autoimmune condition raises the odds of others. Hashimoto's plus a second organ-specific autoimmune disorder may be classified as autoimmune polyglandular syndrome type 3. A workup prompted by this question usually looks wider.
Autoimmune gastritis raises the risk of stomach cancer, and that risk is still small. A 2026 analysis put the increase at roughly double, while older work put it closer to eleven times. Stomach cancer is uncommon to begin with, so the absolute risk stays low even when it is multiplied.
Risk was lowest in people who were only antibody-positive. It was highest in those who had developed pernicious anemia, and it rose after 60.
An upper endoscopy is used to see how much of the stomach is affected and to check for changes over time. Autoimmune gastritis is one form of atrophic gastritis, the general term for a stomach lining that has thinned and lost its working cells. Long-term H. pylori infection is the other common cause. The American Gastroenterological Association suggests considering a repeat endoscopy every three years in advanced atrophic gastritis. For the autoimmune form specifically, the association says the best interval is not established. The schedule belongs with a gastroenterologist who knows your case.
A woman can spend years being treated for the wrong thing. The label might be irritable bowel syndrome, or SIBO, or an H. pylori infection that keeps coming back, or a thyroid that keeps needing medication adjustments. The iron and B12 driving how she feels stay low the whole time. If autoimmune gastritis is what is behind it, none of that treatment reaches the reason the deficiencies keep returning.
Iron and B12 deficiency can both be treated once the reason for them is known. The first round of testing is often a blood draw, and some people also need an upper endoscopy. Any one of these is a reason to ask about autoimmune gastritis. Iron that will not stay up is one. So is a TSH that will not stabilize, post-meal fullness that keeps getting relabeled, or a B12 drifting toward the bottom of the range.
Book a Discovery Call if your thyroid is managed and you still do not feel like yourself. It is a complimentary 30-minute screening call to work out whether Indigo is the right fit. Booking it does not commit you to treatment. Indigo Integrative Health Clinic is an integrative and functional medicine practice serving patients across DC, Maryland, and Virginia. We deliver care by telehealth, and we provide IV therapy and injections in person at our clinic in the heart of Georgetown. If we cannot help, we will say so on the call.
This content is provided by Indigo Integrative Health Clinic for educational purposes only. It does not constitute medical advice, a diagnosis, or a treatment recommendation, and does not establish a provider-patient relationship. Individual health conditions vary — information presented here may not apply to your specific situation. Always consult a qualified, licensed healthcare provider before making decisions about your health, medications, supplements, or treatment plan.


A thyroid panel and a standard blood count do not diagnose autoimmune gastritis, an immune attack on the acid-producing cells of the stomach. It is about five times more common in people with autoimmune thyroid disease. That includes both Hashimoto's and Graves' disease. It often surfaces as iron deficiency that does not correct, with B12 deficiency following later.

Bartonella is a bacterial infection that often appears alongside Lyme. In the US there is no current evidence that ticks transmit it, and the question is still under investigation. The proven routes are cat scratches and bites, cat-flea feces, and body lice. It is hard to detect, which is why a thorough Lyme workup checks for it properly.
Babesia is a malaria-like parasite carried by the same tick that carries Lyme. Because it is a parasite and not a bacterium, the antibiotics typically used for Lyme have no effect on it. It is seldom tested for, so people can finish Lyme treatment, still feel sick, and not understand why.

Hours of Operation
Monday - Friday
9am - 5pm

